Vitrectomy Surgery: A Complete Patient Guide to the Procedure, Recovery and Results
2 November 2026 · 7 min read
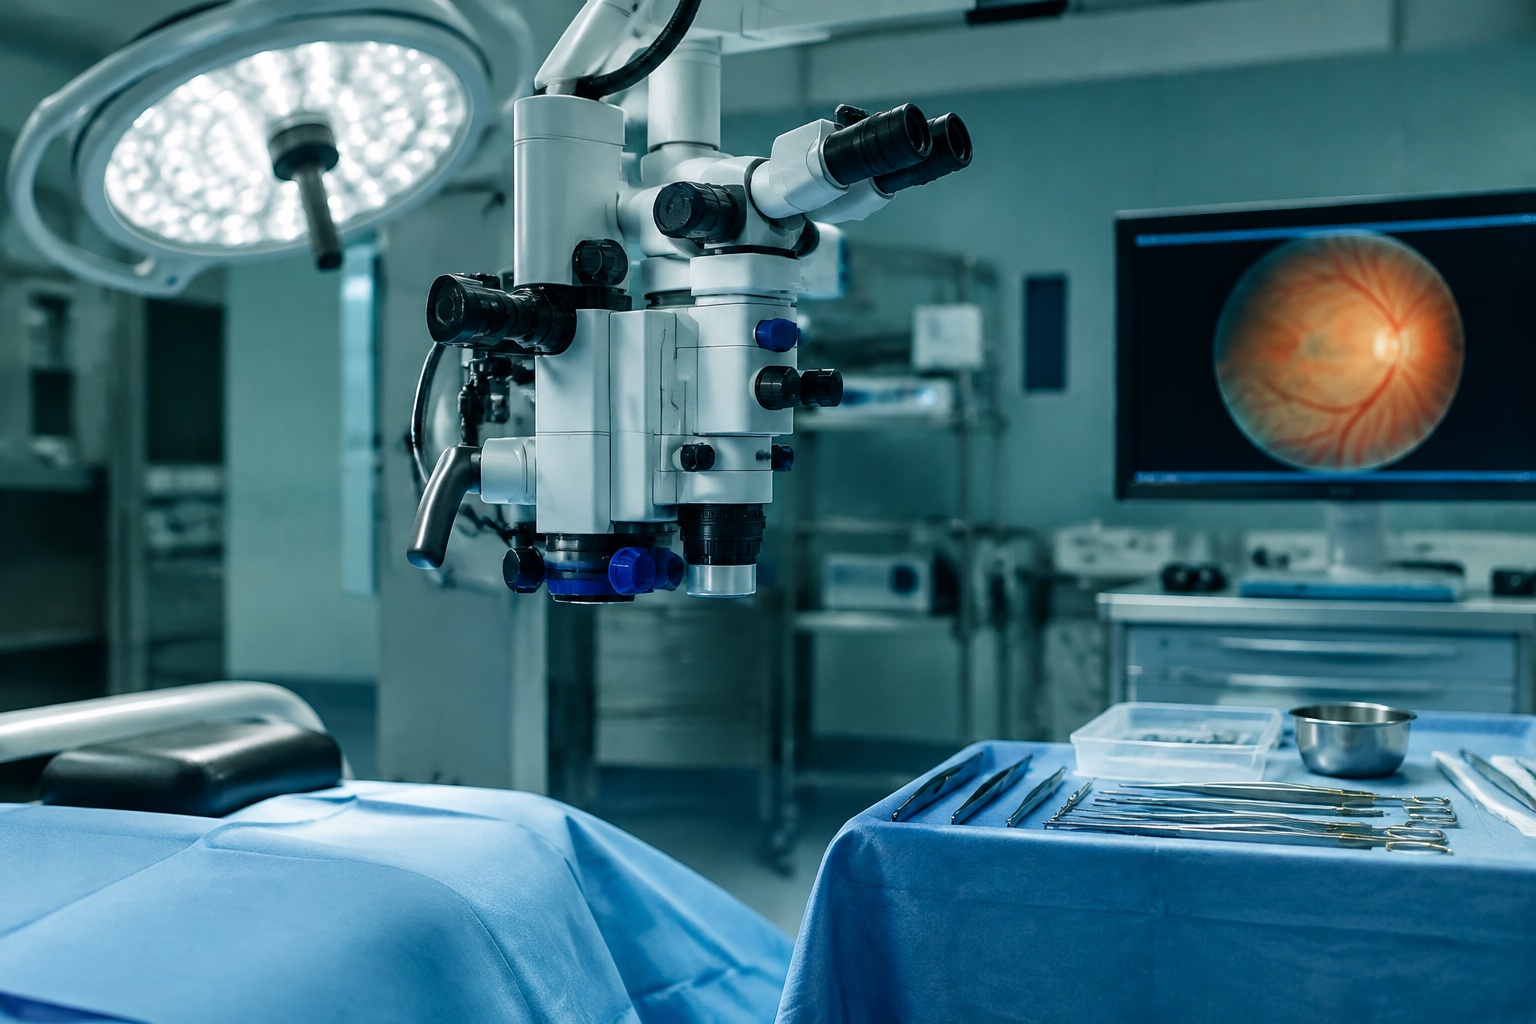
If you have been told that you may need an operation at the back of your eye, the word "vitrectomy" can sound daunting. It is natural to have questions about what the surgery involves and how recovery works. This guide walks you through each stage in clear, practical language so that you can go into your consultation feeling informed rather than anxious.
Put simply, Vitrectomy Surgery is a microsurgical procedure in which the clear vitreous gel that fills the back of the eye is carefully removed and replaced with a saline solution, a gas bubble or silicone oil. It is one of the most frequently performed operations in retinal surgery, and it allows the surgeon to work directly on the retina, the delicate light-sensitive layer that lines the inside of the eye and makes sight possible.
Understanding the Vitreous and the Retina
To understand why a vitrectomy may be recommended, it helps to know a little about the anatomy of the eye. Behind the lens sits a large cavity filled with the vitreous, a transparent gel made mostly of water, collagen fibres and hyaluronic acid. In childhood the vitreous is firm and evenly attached to the retina. Over the decades it slowly becomes more liquid and begins to shrink away from the retinal surface.
What the vitreous gel does
In adulthood the vitreous plays a minor role. Light passes through it on the way to the retina, but the eye can function perfectly well without it. This is why the gel can be removed safely and replaced with another substance without harming sight.
Why the vitreous can sometimes cause problems
As the gel shrinks it usually peels away from the retina harmlessly, a process called posterior vitreous detachment. In some people, however, it pulls on the retina as it separates, creating a tear or a hole. In others, the gel becomes clouded with blood or inflammatory cells, or thin sheets of scar tissue form on the retinal surface. In each of these situations, removing the vitreous gives the surgeon access to repair the underlying problem and clears the visual pathway.
When Is a Vitrectomy Recommended?
A vitrectomy is a versatile operation and is used for a wide range of conditions affecting the back of the eye. Common reasons include:
- Retinal detachment, where the retina lifts away from the wall of the eye. Our guide to the warning signs of retinal detachment explains how to recognise this emergency.
- Macular hole and epiretinal membrane, which distort or blur central vision. You can read more in our article on macular hole and epiretinal membrane treatment.
- Vitreous haemorrhage, often linked to advanced diabetic retinopathy, where bleeding into the gel prevents light from reaching the retina.
- Severe, persistent floaters that significantly interfere with daily life. Most floaters are harmless, and our guide on when floaters and flashes need attention explains the difference.
- Eye infection (endophthalmitis), injury or fragments of lens material left behind after complicated cataract surgery.
The decision to operate always depends on the individual. Some conditions need urgent treatment within hours or days, while others can be monitored and treated only if vision deteriorates.
Before Surgery: Assessment and Preparation
Your journey begins with a detailed assessment by a Consultant Ophthalmologist with experience in retinal disease. This usually includes a vision test, eye pressure measurement, dilating drops to widen the pupil, and a careful examination of the retina using a slit lamp microscope.
Imaging plays a central role. Optical coherence tomography (OCT) produces cross-sectional pictures of the retina, a little like an ultrasound but using light, and shows fine detail such as holes, membranes or fluid. If the view into the eye is blocked by blood or a dense cataract, an ultrasound scan can help assess whether the retina is attached.
Before the operation you will normally be asked about your general health, the medicines you take and any allergies. Blood thinners, diabetes control and blood pressure are all relevant. Arrange for someone to take you home on the day.
What Happens During a Vitrectomy?
Most vitrectomies take between thirty minutes and two hours, depending on complexity. The operation is usually carried out as a day case, which means you can go home the same day.
Anaesthesia
Many patients have the operation under local anaesthetic. Numbing drops are applied first, followed by an injection of anaesthetic around the eye, so you should not feel pain during the procedure. You remain awake, aware mainly of light and gentle pressure. A general anaesthetic may be suggested for longer operations or for patients who would find it difficult to lie still.
The micro-incision technique
Modern vitrectomy uses tiny instruments passed through three small ports in the white of the eye. These openings are so small that they often seal by themselves without stitches. Working under a high-powered operating microscope, the surgeon uses a fine cutting and suction instrument to remove the vitreous gel. Depending on the condition, they may then peel scar tissue, seal tears with laser, or remove blood and debris.
Tamponade: saline, gas or silicone oil
At the end of the operation the eye is filled with a substance that supports the retina while it heals. This is called a tamponade:
- Saline is used when no extra support is needed. The eye naturally replaces it with its own fluid.
- A gas bubble presses gently against the retina to hold tears or holes closed. It is absorbed slowly over a few weeks, depending on the type of gas used.
- Silicone oil provides longer-term support in complex cases. It does not dissolve and usually needs a second, smaller operation to remove it at a later date.
Recovery After Vitrectomy
Recovery is gradual, and patience is important. Vision is usually very blurred at first, particularly if a gas bubble or oil has been used.
The first few days
You will go home with a protective shield and a course of eye drops to reduce inflammation and prevent infection. Mild discomfort, a gritty feeling, redness and watering are common and usually settle within one to two weeks. Simple painkillers are often enough. Severe pain, increasing redness or worsening vision should be reported to the eye unit straight away.
Posturing
For some conditions, particularly macular holes and certain retinal detachments, you may be asked to keep your head in a specific position for part of each day. This helps the bubble rise and press on the right part of the retina. Your surgical team will explain exactly how long and how often posturing is needed, as instructions vary.
Important gas bubble precautions
If gas has been placed in your eye, you must not fly or travel to high altitude until it has fully disappeared, because the bubble can expand dangerously as air pressure falls. You should also tell any doctor or anaesthetist that you have gas in your eye, as nitrous oxide anaesthesia can cause the bubble to expand.
Returning to work and driving
Desk-based work may be possible within one to two weeks, while heavy lifting and strenuous activity may need to wait longer. You should not drive until your surgeon confirms that your vision meets the legal standard for driving.
Risks and Possible Complications
Like all surgery, vitrectomy carries some risks, and a good surgeon will discuss them openly. The most common long-term effect is faster development of cataract in people who still have their natural lens. Many patients eventually need cataract surgery within a few years. Other possible complications include raised eye pressure, a new retinal tear or detachment, bleeding and, rarely, infection. Serious complications are uncommon.
Results and Long-Term Outlook
The visual outcome depends largely on the condition being treated and how long it was present before surgery. When blood is cleared from the vitreous, improvement can be dramatic. With macular holes and membranes, vision often improves steadily over several months. In retinal detachment, the main aim is to save the eye's sight, and early treatment, before the central retina is affected, gives the best chance of a good result.
Questions to Ask Your Surgeon
Before agreeing to surgery, it is reasonable to ask:
- What is the aim of the operation in my case?
- Which type of tamponade will be used, and how will it affect my daily life?
- Will I need to posture, and for how long?
- How soon can I return to work, exercise and driving?
- What are the most relevant risks for me?
Final Thoughts
A vitrectomy is a precise, well-established operation that has transformed the outlook for many people with serious retinal conditions. Understanding what to expect at each stage can make the experience far less stressful. If you notice sudden changes in your vision, do not wait. Early assessment by an eye specialist gives you the widest range of treatment options and the best chance of protecting your sight for the future.
This article is for general information and does not replace a personal consultation. If you notice sudden changes in your vision, contact your optometrist, an eye casualty department or NHS 111 the same day.
Related Articles

Retinal Detachment: Warning Signs, Causes and Treatment Options
Floaters, flashes and a shadow across your vision can signal an emergency. Learn the signs and why fast treatment matters.

Eye Floaters and Flashes: When Should You See an Eye Specialist?
Most floaters are a normal part of ageing — but some changes need same-day attention. Here is how to tell the difference.

Diabetic Retinopathy: How Diabetes Affects Your Eyes and How to Protect Your Sight
Diabetic eye disease is often silent in its early stages. Discover how screening and modern treatment help protect your vision.

Macular Hole and Epiretinal Membrane: Symptoms, Diagnosis and Surgical Treatment
Wavy lines and blurred central vision can point to a macular hole or membrane. Learn how OCT diagnosis and surgery can help.